Compliant consumers
Stable this week94%
KuhstomDataGPT connects the information already spread across your EHR, billing, claims, workforce, compliance, and internal reports — then helps your organization continuously detect risk, protect revenue, and improve operations.
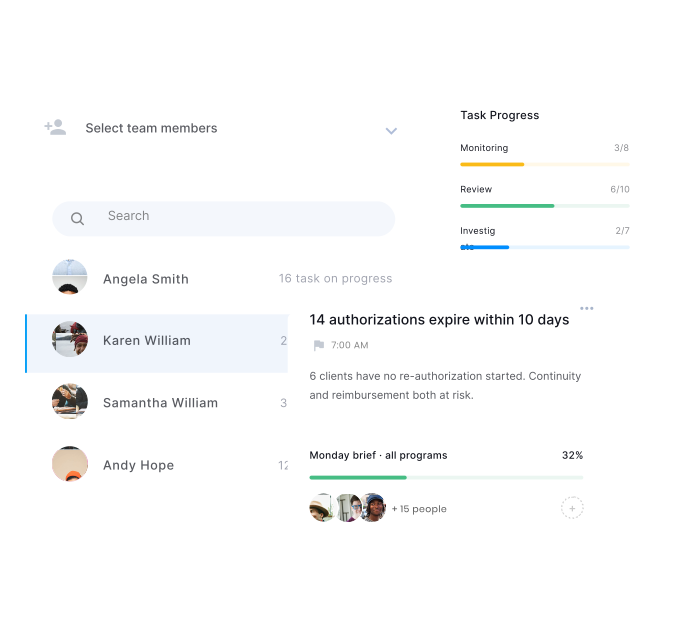

Ask questions. Monitor KPIs. Detect risks. Automate reporting. Act earlier.

KDG brings information into one clear view, helping teams understand what is happening across their operations and act on it faster.
Providers are managing patient care, scheduling, billing, outcomes, and compliance across systems that were never designed to work together.
Your EHR was built to manage care. Your billing system was built to process claims. Your workforce system manages staff. Your spreadsheets fill the gaps. Leadership still waits on someone to assemble the answer by hand.

What is approaching, missing, or overdue
Where dollars are leaking and why
What patterns need attention this week
What changed, and what to do about it
Each area is configured to your programs, policies, and thresholds, then monitored continuously instead of assembled on request.
3 of 6 teams are below productivity target. Community care is 11 points under, driven by caseload; Youth services by missed visits; and Outpatient by incomplete documentation... more
Productivity vs target
Target 80% · week of Oct 26
| Team | Productivity | Primary driver | Weeks below |
|---|---|---|---|
| Community care | 68% | Caseload | 6 wks |
| Youth services | 74% | Missed visits | 3 wks |
| Outpatient | 79% | Documentation | 2 wks |
| School-based | 96% | — | 0 wks |
Longest gap: Community care — 6 weeks below target.
Outpatient collections fell 18% in October to $292K. Two payer patterns explain most of it: bundled service codes on 41 claims and a documentation hold on $42.6K... more
Outpatient collections
$K · Jun–Oct
Two payer patterns account for 61% of the drop.
9 encounters this week are not billing-ready. 4 are missing signatures, 3 have notes older than 72 hours, and 2 need corrected service codes... more
Not billing-ready this week
Week of Oct 26 · 9 encounters across 3 programs
| Consumer | Clinician | Missing item | Age |
|---|---|---|---|
| Jordan Lee | Morgan R. | Note signature | 3 days |
| Avery Brooks | Casey M. | Service code | 1 day |
| Taylor Quinn | Jamie T. | Note not linked | 4 days |
| Riley Morgan | Morgan R. | Late note | 5 days |
Draft reminders to the 4 clinicians
Show documentation gaps by program
Consumers at risk
Grouped by program · next 14 days
| Consumer | Program | Requirement | Due |
|---|---|---|---|
| Jordan Lee | Outpatient | Treatment plan review | 3 days |
| Avery Brooks | Outpatient | Assessment update | 6 days |
| Taylor Quinn | Community care | Service frequency | 5 days |
| Riley Morgan | Community care | Treatment plan review | 8 days |
| Cameron Ellis | Youth services | Assessment update | 11 days |
| Parker Reed | Youth services | Required service | 13 days |
74 of 128 authorizations are current. 26 expire in the next 10 days, 11 are expected to exhaust their approved units first, and 17 have already lapsed... more
Authorization status
128 authorizations · next 10 days
Closest to lapse: Jordan Lee — 3 days left, 18 units, $2,450 at risk.
I found 12 consumers below expected service frequency, with the largest gap in Community Care. Missed visits and staffing coverage changes overlap there, while Outpatient attendance declined across two locations. The pattern is strongest among consumers scheduled for weekly services... more
Which programs have the highest missed-visit rates?
Are staffing gaps linked to lower service frequency?
Which consumers need outreach this week?
12 records carry the highest audit risk tomorrow. 5 are missing required evidence, 4 contain conflicting dates, and 3 prior Q2 findings are still open... more
Highest-risk records
If an audit started tomorrow · 12 records across 3 programs
| Consumer | Program | Risk | Missing evidence | Prior finding |
|---|---|---|---|---|
| Jordan Lee | Outpatient | High | Treatment plan signature | Q2-04 open |
| Riley Morgan | Outpatient | High | Units vs authorization | Q2-04 open |
| Avery Brooks | Community care | Medium | Note not linked to claim | None |
| Taylor Quinn | Youth services | Medium | Assessment 4 days late | Q2-07 open |
Leadership briefing · October
One month in: denials are down, but three signals need a decision before month end.
What changed this month
Show denials by payer this month
Model next month if overtime holds
KuhstomDataGPT is not an EHR replacement and not a new place for your team to do their work. It reads what your systems already produce and returns answers into the workflow you have.

API, database connection, secure file transfer, data warehouse access, or an approved export workflow.
Most behavioral health data reaches us one way or another. Bring us the hard one.
Every named system is labeled Native, API, File export, Custom, In pilot, or Planned. No one-click promises we can't keep.
Clinical workflow is untouched.
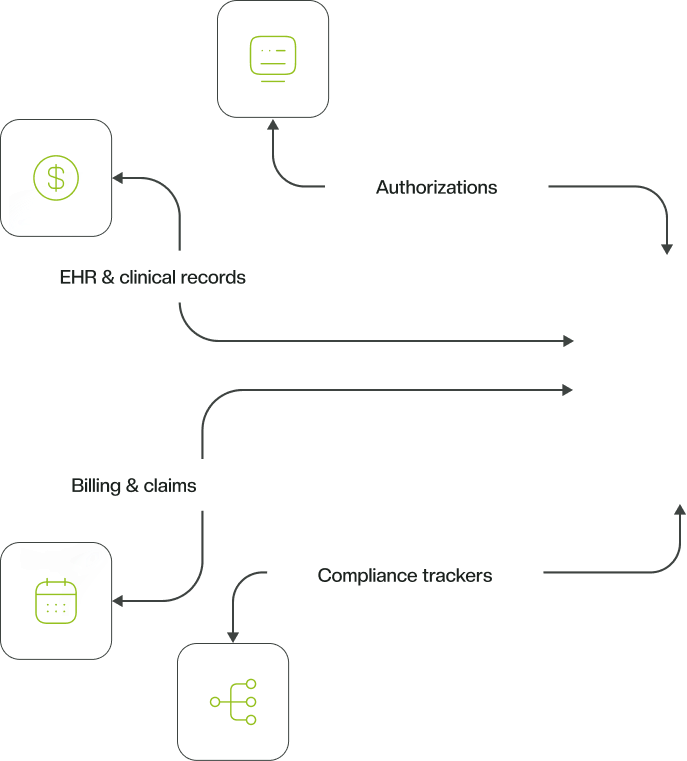
KuhstomDataGPT pulls your files, databases, APIs, and enterprise systems into one connected view while keeping your existing tools intact.










Notes, plans, assessments
Encounters, denials, payments
Approved units, expiry dates
Caseloads, visits, productivity
Requirements, due dates

Outpatient • Clinician: Morgan R.
Treatment plan
Current - review due in 3 days
Authorization
Active - 12 units remaining
Last encounter
Oct 30 - note on file
Billing status
1 item needs attention
Your programs, payers and policies, mapped to your data.
every 180 days
every 180 days
minimum per plan
within 72 hours
no auth, no billing
Outpatient • Clinician: Morgan R.
Active compliance schedule automatically mapped from Outpatient protocol
Not a generic deadline. Yours. Mapped by program, payer, and policy, so the date KDG watches is the date your auditor will use.
Recurring analysis runs automatically against the KPIs you configure. No one has to remember to pull this report. KDG checks it every morning, on the schedule you set.
Exceptions and unusual patterns surface as they appear, including threshold breaches defined by your own rules in Configuration.
Not billing-ready · flagged this morning
Encounter Oct 30 · 3 days old · Morgan R.
The claim cannot be assembled until it is linked.
Falls out of compliance if it is not completed.
9 encounters
not billing-ready across 3 programs
Same pattern in three programs - a workflow issue, not one clinician.
Ask why in plain language, and follow the evidence to the record.
Jordan is at risk for two reasons: the Oct 30 encounter note is unsigned, so it is not billing-ready, and the treatment plan review is due in 3 days under the Outpatient rule. The unsigned note is the immediate billing issue; completing the review before its due date will keep the plan current. The authorization is active, with 12 units remaining, so coverage is not the cause of the billing risk.
Encounter note — Oct 30
Status: unsigned · Clinician: Morgan R.
Treatment plan — Mar 12
Rule: review every 180 days · Due in 3 days
Authorization — Active
12 units remaining · Service is covered
Prioritized lists and alerts go straight to the people who own the work.
| Assignee | Task description | Due date | Action |
|---|---|---|---|
 Morgan R.Clinician | Get Jordan Lee's Oct 30 note signed | Due today | |
 Casey M.Admin Staff | Correct service code - Avery Brooks | Tomorrow | |
 Jamie T.Clinical Lead | Link note to encounter - Taylor Quinn | Tomorrow |
One layer, four very different jobs. The executive view.
Outpatient up · Community Care down 11 points vs target
12 records at audit risk · 3 prior findings still open
9 encounters not billing-ready this week
One page, ranked by impact, not six separate reports
By program, payer, and team
Every number traces back to its source record
Leadership decides on Monday instead of waiting for the report.
One layer, four very different jobs. The compliance view.
Treatment plan review due in 3 days
Assessment update due in 6 days
Service frequency below plan
Missing evidence named on each record
Q2-04 and Q2-07, owners assigned
Listed before an auditor finds them
No audit scramble. The evidence list is already maintained.
One layer, four very different jobs. The revenue view.
Documentation: 8 of this week's 9 blocked encounters
6 expire in 14 days, with revenue attached to each
A pattern flagged across 3 programs
The biggest recoverable amount sits on top
Clinician, biller, or supervisor, named
Signature, code, or link, stated plainly
Billing-ready is a daily list, not a month-end surprise.
One layer, four very different jobs. The operations view.
Target 80% · Driver: caseload · 6 weeks below
Driver: missed visits · 3 weeks below
Driver: incomplete documentation · 2 weeks
Named, and grouped by program
Where they cluster, and for which teams
So support goes where the load actually is
Supervisors coach from facts, not from the loudest anecdote.
Detailed posture, including HIPAA safeguards, BAA availability, subprocessors, and audit status, is published on the Security page and confirmed with your team during diligence.
API, database connection, secure file transfer, data warehouse access, or an approved export workflow.
Role-based access, SSO, tenant permissions, and administrative controls.
User, query, workflow, and administrative activity is recorded and reviewable.
Documented data flow, retention, and deletion, including what providers can and cannot receive.
Your organization's data stays separated from every other customer's.
A clear, contractual statement on whether customer data is ever used to train models.

SOC 2 Type II
Certified

HIPAA
Ready

ISO 27001
Certified
We'll map the data, questions, monitoring logic, and pilot measures around your organization.
Book a Behavioral Health Demo